Pectus Carinatum
What Is Pectus Carinatum (Pigeon Chest)? Detailed Information on Symptoms, Diagnosis, Bracing, Exercise, and Surgical Options.
Pectus Carinatum (Pigeon Chest) What Is It?
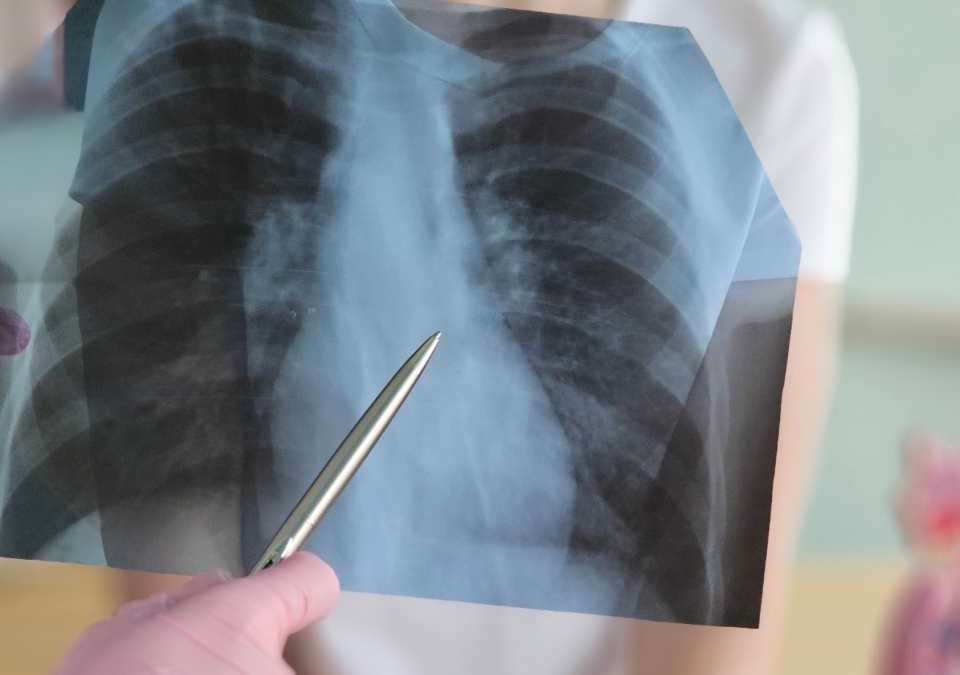
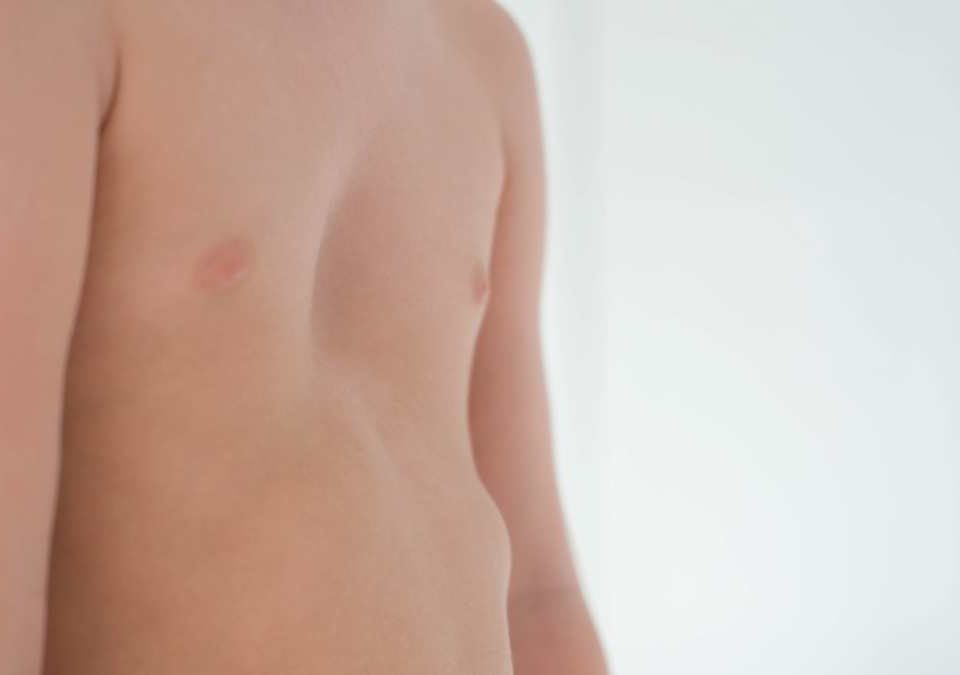
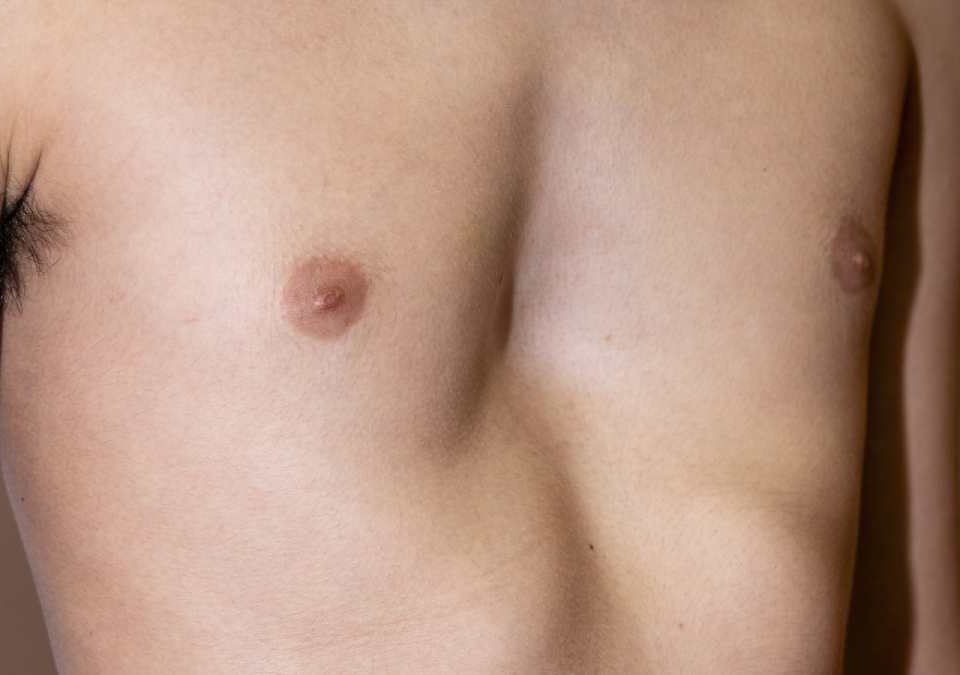
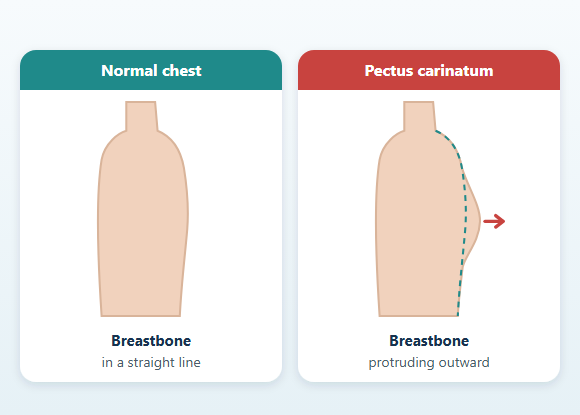
Pectus carinatum is a developmental chest wall deformity characterized by an outward protrusion of the breastbone and the front of the chest wall. It is also known as "pigeon chest" or "protruding chest." The deformity may be limited to a specific part of the breastbone, or it may affect a wider area of the front chest wall. In some people the protrusion is centered and symmetric, while in others it is more prominent on the right or left side due to rotation of the sternum. Pectus carinatum may be noticed in early childhood, but it most often becomes more prominent during the rapid growth of adolescence. Mild deformities may cause only a difference in the appearance of the chest. Some people, however, may experience tenderness in the chest area, postural changes, discomfort during exercise, or psychosocial effects related to body image. Treatment is not necessary for every patient and is not based on a single method. The evaluation considers the type of deformity, the flexibility of the chest wall, age, whether growth is ongoing, physical complaints, and psychosocial impact together. In children and adolescents with a flexible chest wall, a compression brace is one of the main non-surgical treatment options. Surgical methods may be considered for rigid, advanced, or complex deformities, or for selected patients who have not responded adequately to properly applied bracing.
What Is Pectus Carinatum?
- Protrusion of the lower part of the breastbone
- Broad protrusion of the middle of the chest
- Prominence of the upper part of the breastbone
- Greater protrusion on the right or left side
- Rotation of the sternum
- Protrusion on one side and a depression on the other
- Flaring of the lower rib margins
- Mixed deformity combined with pectus excavatum
What Causes Pectus Carinatum?
Is Pectus Carinatum Hereditary?
- Pectus excavatum
- Rib cage asymmetries
- Scoliosis
- Joint laxity
- Certain connective tissue disorders
However, the absence of a chest wall deformity in other family members does not mean that pectus carinatum will not develop. The type and severity of the deformity can also differ among members of the same family.
When Does Pectus Carinatum Become Noticeable?
- The chest protrusion may increase
- The difference between the right and left sides may become more noticeable
- Rotation of the sternum may become more visible
- Flaring of the lower rib margins may develop
- Postural changes may appear
- Accompanying scoliosis may be noticed
- The impact on body image may increase
What Are the Types of Pectus Carinatum?
What Are the Types of Pectus Carinatum?
Chondrogladiolar Pectus Carinatum
This is the most common type. The protrusion is usually located in the middle or lower part of the sternum. It may be symmetric or more prominent on one side. A compression brace may be considered in patients whose chest wall is sufficiently flexible.Chondromanubrial Pectus Carinatum
This type is characterized by forward prominence of the manubrium, the upper part of the sternum, and the upper costal cartilages. It is less common than the chondrogladiolar type. In some patients the chest wall may be more rigid, and the anatomy of the deformity may be more complex. The treatment plan is determined by the flexibility of the chest wall and the structure of the deformity. Although bracing may be considered in selected patients, surgical options may come into consideration for rigid or complex deformities.Asymmetric and Mixed Deformities
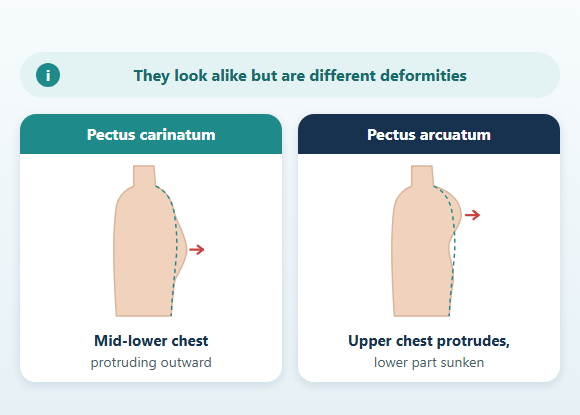
In some patients, one area of the chest wall protrudes outward while another area is depressed. The sternum may be rotated, or the protrusion may be more prominent on one side. Such deformities may combine features of pectus carinatum, pectus excavatum, sternal rotation, and rib asymmetry. The evaluation of mixed deformities may be more detailed than that of standard symmetric pectus carinatum.Are Pectus Arcuatum and Pectus Carinatum the Same?
- The upper sternum may protrude forward
- The lower sternum may be displaced inward
- A distinct angle may form in the sternum
- The chest wall may be more rigid
- The response to standard pectus carinatum treatments may differ
What Are the Symptoms of Pectus Carinatum?
- Tenderness over the protruding area
- Pain or a feeling of tightness in the chest area
- Discomfort when lying face down
- Sensitivity to clothing or equipment that touches the chest
- Postural changes
- Rounded shoulders
- Musculoskeletal complaints in the back, neck, or shoulders
- Shortness of breath or a feeling of tiring quickly during exercise
- Psychosocial effects related to body image
Shortness of breath, palpitations, chest pain, or reduced exercise capacity are not specific to pectus carinatum. Asthma, poor fitness, anemia, heart rhythm problems, and various musculoskeletal problems can cause similar complaints. For this reason, symptoms should not automatically be attributed to the chest deformity.
Does Pectus Carinatum Affect the Heart?
Does Pectus Carinatum Affect the Lungs and Exercise Capacity?
- The structure and mobility of the rib cage
- Posture
- Physical fitness
- Accompanying respiratory conditions such as asthma
- Heart disease
- Anemia
- Avoidance of physical activity
In people with significant exercise-related complaints, the necessary tests are planned based on the clinical evaluation.
Does Pectus Carinatum Affect Posture?
- Neck and shoulder pain
- Weakness of the back muscles
- Tightness of the chest muscles
- Changes in shoulder blade movement
- Reduced mobility of the rib cage
Exercise and physical therapy can help improve posture, but they are not expected to fully correct the structural chest protrusion on their own.
Can Pectus Carinatum Have Psychological Effects?
- Neck and shoulder pain
- Weakness of the back muscles
- Tightness of the chest muscles
- Changes in shoulder blade movement
- Reduced mobility of the rib cage
What Conditions Can Occur Together with Pectus Carinatum?
- Scoliosis
- Kyphosis
- Shoulder asymmetry
- Joint laxity
- Marfan syndrome
- Ehlers-Danlos syndrome
- Noonan syndrome
- Certain congenital heart diseases
- Mixed chest wall deformities
Is There a Link Between Pectus Carinatum and Scoliosis?
- The shoulders may appear at different levels
- One shoulder blade may be more prominent
- Trunk rotation may be present
- The two sides of the rib cage may look different
How Is Pectus Carinatum Diagnosed?
- The location of the protrusion
- Its width and height
- Whether it is symmetric or asymmetric
- Rotation of the sternum
- Flexibility of the chest wall
- How much it can be corrected with pressure
- Other areas of depression
- Flaring of the lower rib margins
- Shoulder and back posture
- Signs of scoliosis
- Pain or tenderness
In patients for whom a compression brace is planned, the flexibility of the chest wall and how much the protrusion can be corrected with controlled pressure are particularly important.
Why Is Chest Wall Flexibility Important?
- Assessing suitability for bracing
- Planning the pressure to be applied
- Monitoring the course of treatment
- Preventing the application of excessive pressure
The chest wall generally becomes more rigid as growth is completed, but chronological age alone does not determine suitability for brace treatment.
What Tests Are Done for Pectus Carinatum?
- Chest X-ray
- Computed tomography
- Magnetic resonance imaging
- Electrocardiography
- Echocardiography
- Pulmonary function tests
- Cardiopulmonary exercise testing
- Scoliosis X-rays
- Three-dimensional surface scanning
- Standardized photographic assessment
Computed tomography is not always necessary to diagnose typical, uncomplicated cases of pectus carinatum. Imaging methods that involve ionizing radiation should be used only when medically necessary, especially in children.
When Can Computed Tomography Be Used?
- In complex or markedly asymmetric deformities
- When pectus arcuatum is suspected
- In mixed pectus deformities
- When a detailed assessment of sternal and rib anatomy is required
- For surgical planning
- If there has been previous chest wall surgery
Three-Dimensional Surface Scanning
How Is the Severity of Pectus Carinatum Determined?
- Height of the protrusion
- Width of the affected area
- Symmetry
- Sternal rotation
- Chest wall flexibility
- Pressure required for correction
- Change in the deformity over time
- Pain or tenderness
- Effects on posture
- Psychosocial impact
- Age and growth status
- Previous treatments

Does Pectus Carinatum Progress Over Time?
Pectus carinatum may become more prominent, especially during periods of rapid growth. During follow-up, chest appearance, symmetry, growth, chest wall flexibility, posture, and any accompanying spinal changes may be assessed. As growth is completed, the chest wall may become more rigid and more fixed. In some patients, this can make correction with a brace more difficult. Not every mild pectus carinatum deformity is expected to progress.Does Every Case of Pectus Carinatum Need Treatment?
No. Deformities that are mild, not progressing, not causing physical complaints, and not significantly affecting the person psychosocially may simply be monitored. Treatment may be considered in situations such as:- Progression of the deformity
- Pain or tenderness in the chest area
- Significant postural changes
- Impact on daily life
- Avoidance of sports or social activities
- Significant impact on body image
- The patient being well informed about treatment and having realistic expectations
Can Exercise Correct Pectus Carinatum?
Exercise does not eliminate the structural cause of pectus carinatum. However, appropriate exercise programs can:- Improve posture
- Help correct shoulder position
- Strengthen the back muscles
- Increase the flexibility of the chest muscles
- Improve breathing control
- Support overall physical fitness
What Is the Role of Physical Therapy in Pectus Carinatum?
Physical therapy can help improve posture and muscle balance in particular. Although the program varies from patient to patient, it may include:- Posture exercises
- Strengthening of the muscles around the shoulder blades
- Stretching of the chest muscles
- Strengthening of the back muscles
- Diaphragmatic breathing
- Rib cage mobility exercises
- General conditioning exercises
What Is a Pectus Carinatum Brace?
A compression brace is a non-surgical treatment that applies controlled pressure to the protruding area in pectus carinatum, with the aim of gradually reshaping the chest wall over time. A brace generally includes:- A frame that wraps around the chest
- A pressure pad placed over the protrusion
- A support area on the opposite side
- A mechanism for adjusting the pressure
What Is a Dynamic Compression System?
Dynamic compression systems are brace systems that allow the pressure applied to the chest wall to be measured and adjusted in a controlled way. These systems can help with:- Assessing chest wall flexibility at the start
- Adjusting the pressure to be applied
- Avoiding excessive pressure
- Reducing skin problems
- Monitoring treatment progress
Who May Be a Candidate for Brace Treatment?
A compression brace may be considered particularly in patients:- Whose chest wall is flexible
- Who are still growing
- Whose protrusion can be corrected with controlled pressure
- Who can adhere to regular brace use
- Who have no active skin problem that prevents pressure from being applied
Who May Not Be a Candidate for Brace Treatment?
The effectiveness of brace treatment may be limited in situations such as:- A very rigid chest wall
- Severe asymmetry
- Mixed pectus deformity
- Certain chondromanubrial or pectus arcuatum configurations
- An open wound or active skin problem in the area where pressure will be applied
- Pain that cannot be tolerated
- Inability to adhere to regular use
- Inadequate response to previous, properly applied brace treatment
How Many Hours a Day Is the Brace Worn?
The duration of brace use is not the same for all patients. The daily wearing time may vary depending on factors such as:- Age
- Chest wall flexibility
- Structure of the deformity
- Pressure applied
- The brace system used
- Skin tolerance
- Whether the patient is in the active correction or maintenance phase
- Daily living circumstances
How Long Does Brace Treatment Last?
The total length of treatment varies from person to person. Age, chest wall flexibility, the size of the deformity, the pressure required for correction, daily wearing time, adherence to treatment, and ongoing growth can all affect the duration. In some patients, noticeable change may be seen within a few months, while the overall treatment and maintenance process may take longer. Early improvement in the appearance of the chest does not mean that treatment is complete.Active Correction Phase
During this phase, the purpose of the brace is to reduce the chest protrusion. The shape of the chest wall, the pressure applied, the skin, and adherence to treatment are monitored regularly.Maintenance Phase
Once adequate correction has been achieved, the wearing schedule may be gradually reduced. The aim is to lower the risk of the deformity becoming prominent again, especially while growth is still ongoing. When and how treatment is tapered is determined according to the patient's growth status and clinical follow-up.Is Pain Normal While Wearing a Brace?
Mild pressure or discomfort may be felt at first because of the pressure the brace applies. However, the following are not considered normal:- Severe pain
- Numbness
- An open wound
- Blistering
- Bleeding
- Persistent bruising
- Difficulty breathing
- A new change in shape in another area of the chest
Skin Care While Wearing a Brace
Pressure, friction, heat, and moisture can build up between the brace and the skin. It is important to check the skin regularly, keep the brace clean, and avoid wearing it over damp skin for long periods. Mild redness that lasts a short time may occur. However, redness, bruising, blisters, or open wounds that persist after the brace is removed require reassessment of the pressure and the fit of the brace.Is the Brace Worn During Sports?
Whether the brace is worn during sports depends on the brace system and the activity. In sports with a risk of blows to the chest, falls, or contact, the brace can pose a problem for both the wearer and others. If the brace must be removed during sports, the daily wearing schedule can be adjusted according to the treatment plan.What Affects the Success of Brace Treatment?
The main factors that affect the outcome of brace treatment can be listed as:- Chest wall flexibility
- Appropriate patient selection
- A brace that fits the chest structure
- Controlled pressure
- Regular use
- Clinical follow-up
- Early recognition of skin problems
- The patient's participation in treatment
- Completion of the maintenance phase
- Monitoring of growth
Does Brace Treatment Provide Lasting Correction?
In the right patient, brace treatment applied regularly and in a controlled way can provide significant and long-lasting improvement of the chest protrusion. However, the following cannot be guaranteed:- Complete symmetry
- Complete elimination of the deformity
- Completion of treatment within a specific time
- No recurrence
- No need for surgery later on
When Is Surgery Considered for Pectus Carinatum?
Surgery is not the first option for every patient with pectus carinatum. Surgical methods may be considered particularly in selected patients:- Whose chest wall is markedly rigid
- Who are anatomically unsuitable for brace treatment
- Who have not achieved adequate correction despite appropriate and consistent brace treatment
- Who have severe or complex asymmetry
- Who have other anatomical features, such as pectus arcuatum
- Who experience significant physical or psychosocial impact
What Is the Right Age for Pectus Carinatum Surgery?
There is no single age for surgery that applies to every patient. The timing of surgery is determined by taking into account:- The type of deformity
- Whether it is progressing
- Chest wall rigidity
- Suitability for brace treatment
- Results of previous treatments
- Whether growth is ongoing
- The physical and psychosocial impact on the patient
- The planned surgical technique
What Is the Abramson Procedure?
The Abramson procedure is one of the minimally invasive surgical methods used in selected cases of pectus carinatum. In this method, a shaped metal bar is placed in front of the sternum. The purpose of the bar is to apply controlled pressure to the protruding front chest wall and hold the sternum in a more appropriate position. For this reason, the method is sometimes compared to the reverse of the working principle of the Nuss procedure used for pectus excavatum. In the Nuss procedure, the bar supports the breastbone from behind the sternum, pushing it forward, whereas in the Abramson procedure the bar sits in front of the sternum and helps push the protrusion back.How Is the Abramson Procedure Performed?
The operation is performed under general anesthesia. Although the technique may vary according to the patient's anatomy, the procedure generally may include the following steps:- Making small incisions on the sides of the chest
- Shaping the bar to fit the chest structure
- Preparing a passage for the bar in front of the sternum
- Placing the bar on the chest wall
- Using appropriate fixation systems
- Checking the chest protrusion and symmetry
How Long Does the Abramson Bar Stay In?
The length of time the bar stays in the body is not the same for every patient. Age, growth status, chest wall rigidity, the structure of the deformity, the stability of the correction achieved, and follow-up findings all affect the duration. The bar is usually kept in place for an extended period so that the chest wall can adapt to its new shape. The timing of removal is determined based on clinical follow-up.What Are the Risks of the Abramson Procedure?
As with any surgical procedure, there is a possibility of complications with the Abramson procedure. Possible risks include:- Postoperative pain
- Bleeding or hematoma
- Infection
- Displacement or rotation of the bar
- Problems related to fixation materials
- Pressure or irritation of the skin
- Chest wall pain
- Pneumothorax
- Injury to the pleura or lung
- Under- or overcorrection
- Persistent asymmetry
- Recurrence of the deformity
- Need for an additional surgical procedure
- Anesthesia-related complications
What Is the Ravitch Procedure?
The Ravitch method is based on correcting pectus carinatum through open surgery. During surgery, the costal cartilages that contribute to the deformity may be reshaped or partially removed. When necessary, a corrective cut can be made in the sternum to bring the breastbone into a more appropriate position. The Ravitch method may be considered particularly for:- A rigid chest wall
- Marked asymmetry
- Complex deformities
- Pectus arcuatum
- Certain chondromanubrial deformities
- Situations in which minimally invasive methods are not suitable
- Certain deformities that persist despite previous treatments
What Is the Difference Between the Abramson and Ravitch Procedures?
In the Abramson method, a metal bar placed in front of the sternum applies controlled pressure to the chest protrusion. In the Ravitch method, the costal cartilages and, when necessary, the sternum are directly reshaped surgically. The Abramson method is performed using smaller side incisions and a metal bar, while the Ravitch method may allow more direct and extensive anatomical correction. Neither method can be said to be superior to the other for all patients. The surgical technique is chosen according to the anatomical features of the deformity and the patient's clinical condition.Recovery After Pectus Carinatum Surgery
In the early period after surgery, the following are important:- Pain control
- Breathing exercises
- Early mobilization
- Checking the incision sites
- Monitoring the position of the bar, if one was used
- Gradually increasing shoulder and back movements in a controlled way
When Can Sports Be Resumed After Surgery?
The return to sports is planned gradually. In the initial period, walking and light daily activities can be started. As recovery progresses, light cardio, posture exercises, stretching, and controlled strengthening exercises can be added. For contact sports with a risk of blows to the chest and for heavy weight training, the healing of the chest wall and the position of the bar, if present, are taken into account.How Is the Abramson Bar Removed?
When the new shape of the chest wall has become sufficiently stable, the Abramson bar is removed in a separate operation. The procedure is usually performed under general anesthesia. The materials securing the bar are released, and the bar is removed in a controlled manner. Bar removal may be a more limited procedure than the initial corrective surgery, but surgical risks such as bleeding, infection, pain, or injury to surrounding tissues are not completely eliminated.Is Pectus Carinatum Treatment Possible in Adults?
Pectus carinatum can also be evaluated in adults. Because the chest wall is usually more rigid after growth is complete, brace treatment may be more difficult to apply than in children and adolescents. However, brace treatment may be considered in some adults whose chest wall is sufficiently flexible. For rigid, advanced, or complex deformities, surgical methods may come into consideration. The choice of treatment is determined not by age alone, but by the anatomy of the deformity and the flexibility of the chest wall.Can Pectus Carinatum Recur After Treatment?
After brace or surgical treatment, there is a possibility that the chest protrusion may become prominent again. The risk of recurrence may be affected by factors such as:- Ongoing growth
- Stopping brace treatment too early
- Not completing the maintenance phase
- Irregular brace use
- A rigid or asymmetric deformity
- Certain connective tissue disorders
- The adequacy of correction after surgery
- Removal of the bar, if used, before the appropriate time
Will the Chest Be Completely Symmetric After Treatment?
The goal of treatment is to reduce the deformity and achieve a more balanced chest wall appearance. However, perfect symmetry cannot be guaranteed. Sternal rotation, rib asymmetry, scoliosis, differences in muscle development, mixed pectus deformities, and previous surgeries can cause some asymmetry to persist after treatment. For this reason, it is important to assess expectations before treatment in light of the patient's anatomical features.Is Pectus Carinatum Treatment a Definitive Solution?
Brace or surgical treatment can provide significant and long-lasting improvement in suitable patients. However, no method can guarantee:- A completely flat chest appearance
- Perfect symmetry
- Resolution of all physical complaints
- Resolution of all body image concerns
- That the deformity will never recur
- That no complications will occur
Follow-Up After Pectus Carinatum Treatment
The follow-up process varies according to the treatment used. At follow-up visits, the following may be assessed:- Change in the chest protrusion
- Chest wall symmetry
- Flexibility
- Whether growth is ongoing
- Brace wearing time and adherence
- Skin problems
- Recurrence of the deformity
- Incision sites and the status of the bar, if surgery was performed
- Pain
- Posture
- Scoliosis
- Daily life and return to sports
- Psychosocial impact
When Is a Medical Evaluation Needed?
A medical evaluation of the chest wall may be needed in the following situations:- The chest protrusion becoming more prominent over a short period
- A growing difference between the right and left sides
- Persistent or recurrent chest pain
- Significant shortness of breath during exercise
- Palpitations, dizziness, or fainting
- Signs of scoliosis
- Assessing suitability for brace treatment
- Wounds or severe pain related to brace use
- Body image problems that significantly affect daily life
- Recurrence of the deformity after previous treatment
Frequently Asked Questions About Pectus Carinatum
Conclusion
Pectus carinatum is a developmental chest wall deformity that causes the sternum and the front of the chest wall to protrude outward.It usually becomes noticeable in childhood or adolescence, and its appearance can vary from person to person.
Many patients have no serious heart or lung involvement. However, tenderness in the chest area, postural changes, discomfort during exercise, or psychosocial effects related to body image may occur.
The diagnosis is usually made by physical examination. Additional imaging and heart and lung tests are not routine for every patient; they are planned according to clinical need.
In patients with a flexible chest wall, a compression brace is an important non-surgical treatment option. Exercise and physical therapy can be used to support posture, muscle balance, and overall physical fitness.
For selected deformities that are rigid, advanced, complex, or have not responded adequately to appropriate brace treatment, surgical methods such as the Abramson or Ravitch procedure may be considered. Treatment decisions should be made not only on the basis of chest appearance, but by evaluating the anatomy of the deformity, chest wall flexibility, growth status, physical complaints, psychosocial impact, and the person's expectations together.
Disclaimer: The information on this page is provided for general informational purposes only. It does not replace a medical examination, diagnosis, or individualized treatment plan. The evaluation of pectus carinatum and other chest wall deformities may differ depending on the person's age, anatomical features, complaints, and accompanying health conditions.