Does Pectus Excavatum Affect the Heart and Lungs?
Ekim 19, 2026
What Is the Difference Between Thoracic Surgery and Pulmonology?
Ekim 19, 2026
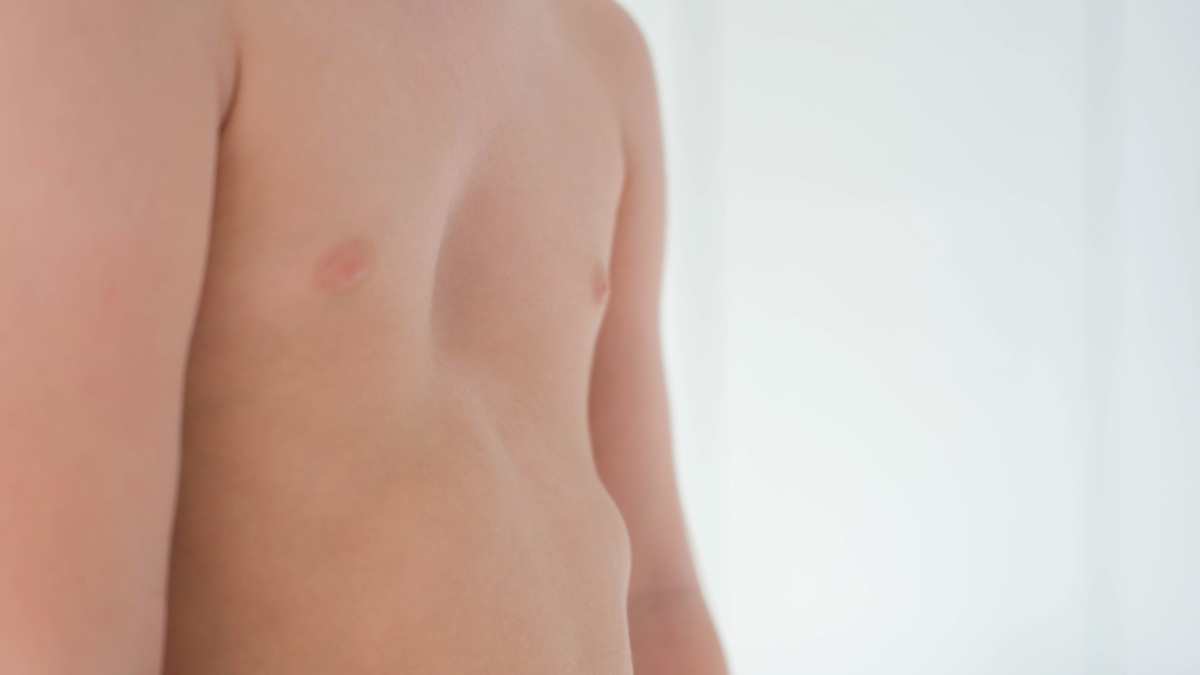
The Nuss procedure is a minimally invasive surgical technique used to correct pectus excavatum, also known as funnel chest.
In pectus excavatum, the breastbone and the front of the chest wall are displaced inward. During the Nuss procedure, a specially shaped metal bar is placed behind the sternum. Once positioned correctly, the bar is rotated so that it lifts the depressed breastbone forward and reshapes the chest wall.
Unlike more traditional open chest wall reconstruction, the Nuss procedure does not usually require a large incision across the front of the chest or routine removal of deformed costal cartilage.
However, the Nuss procedure is not necessary or appropriate for every patient with pectus excavatum.
The decision to operate depends on several factors, including the severity and shape of the deformity, possible effects on the heart and lungs, symptoms, age, chest wall flexibility, and overall health.
Why Is the Nuss Procedure Performed?
The aim of the Nuss procedure is to elevate the depressed sternum and create a more normal chest wall contour.
In some people, pectus excavatum is mild and may not require surgical treatment.
In more pronounced cases, the deformity may:
- alter the position of the heart,
- create mechanical compression on the heart,
- reduce available space within the chest,
- be associated with shortness of breath during exercise,
- contribute to reduced exercise tolerance,
- cause significant psychosocial impact related to chest appearance.
Surgical decisions should therefore not be based only on how deep the chest looks from the outside.
Who May Be Considered for the Nuss Procedure?
The Nuss procedure may be considered in patients with pectus excavatum when surgical correction is thought to be appropriate.
Factors that may be considered include:
- significant chest wall depression,
- progression of the deformity,
- evidence of cardiac compression,
- reduced exercise capacity,
- shortness of breath or early fatigue during activity,
- chest pain or selected cardiopulmonary symptoms,
- substantial psychosocial impact.
The presence of one of these factors does not automatically mean that surgery is required.
The decision is based on the overall anatomical and clinical picture.
What Is the Best Age for the Nuss Procedure?
There is no single age that is appropriate for every patient.
In children and adolescents, the chest wall is generally more flexible, which may make reshaping easier.
For this reason, surgical correction is often considered during adolescence.
However, operating very early is not always necessary. Growth stage, progression of the deformity, symptoms, and chest wall flexibility should all be considered.
The Nuss procedure can also be performed in adults.
Because the adult chest wall is usually more rigid, surgical planning, the number of bars required, pain management, and technical aspects of the operation may differ from those in younger patients.
What Tests Are Performed Before the Nuss Procedure?
Preoperative assessment may evaluate both the external deformity and its possible internal effects.
Depending on the patient, assessment may include:
- physical examination,
- chest imaging,
- CT or other appropriate imaging methods,
- Haller Index or other anatomical measurements,
- electrocardiography,
- echocardiography,
- pulmonary function tests,
- cardiopulmonary exercise testing.
Not every patient requires every test.
The investigations are selected according to age, symptoms, deformity severity, and clinical findings.
Does the Haller Index Determine Whether Surgery Is Needed?
The Haller Index is one of the radiological measurements used to describe the anatomical severity of pectus excavatum.
It compares the internal width of the chest with the shortest distance between the sternum and spine.
A higher Haller Index generally reflects greater narrowing of the chest from front to back.
However, the Haller Index should not be used alone to decide whether surgery is necessary.
Other important factors include:
- symptoms,
- cardiac compression,
- exercise capacity,
- respiratory findings,
- deformity shape,
- asymmetry,
- age,
- general health.
How Is the Nuss Procedure Performed?
The Nuss procedure is performed under general anesthesia.
The basic principle is to place one or more specially shaped metal bars behind the sternum and use them to elevate the depressed chest wall.
The exact technique varies according to anatomy, but the operation generally involves several main steps.
1. Shaping the Pectus Bar
A metal bar of appropriate length is selected before or during surgery.
The bar is then shaped according to the patient’s chest wall and the contour that is intended after correction.
A single standard bar shape is not used for every patient.
Chest width, deformity depth, asymmetry, and chest wall rigidity may all influence bar shape.
2. Making Small Side Incisions
Small surgical incisions are usually made on both sides of the chest.
These incisions allow the bar to be passed across the chest.
One of the reasons the Nuss procedure is described as minimally invasive is that a large incision across the front of the chest is generally avoided.
3. Thoracoscopic Visualization
A thoracoscope, which is a small camera, may be used during the procedure.
This allows the surgeon to visualize:
- the chest cavity,
- lungs,
- heart,
- back surface of the sternum.
Thoracoscopic visualization is particularly important while creating the path behind the sternum.
4. Creating a Safe Path Behind the Sternum
A passage is carefully created behind the breastbone.
This is one of the most technically important steps of the operation because the heart and other major structures lie directly behind the sternum.
The bar is then guided from one side of the chest to the other through this pathway.
5. Positioning and Rotating the Pectus Bar
The specially shaped pectus bar is placed behind the sternum.
It is initially passed in a position that allows it to move safely through the chest.
Once it reaches the correct position, the bar is rotated.
The curved surface of the bar then pushes the sternum forward, correcting the depression.
6. Stabilizing the Bar
The bar must be secured to reduce the risk of unwanted movement or rotation.
The exact fixation method varies.
Depending on the surgical technique, stabilization may involve:
- stabilizers,
- sutures,
- fixation to surrounding chest wall structures.
The aim is to keep the bar in the intended position while the chest wall remodels.
How Many Bars Are Used in the Nuss Procedure?
Not every patient receives a single bar.
One bar may be enough in some cases, while two or more may be required in others.
Multiple bars may be considered especially in:
- wider deformities,
- adult patients,
- long-segment depressions,
- more rigid chest walls.
The number of bars is determined according to anatomy and surgical planning.
What Is the Pectus Bar Made Of?
Pectus bars are surgical metal implants.
Different metal alloys may be used depending on the implant system and the patient.
A history of metal sensitivity or allergy should be discussed before surgery.
Are the Ribs Cut During the Nuss Procedure?
The basic Nuss technique does not involve routinely removing large sections of rib cartilage.
This is one of the main differences between the Nuss procedure and open reconstructive techniques such as the Ravitch procedure.
In the Nuss procedure, the chest wall is reshaped by lifting it from inside with the metal bar.
However, technical details may vary depending on anatomy and previous surgery.
Is the Nuss Procedure Open Surgery?
The Nuss procedure is generally described as minimally invasive repair of pectus excavatum.
Small incisions are made on the sides of the chest, and thoracoscopic visualization may be used.
However, calling the operation “minimally invasive” does not mean it is a minor or risk-free procedure.
Passing a metal bar behind the sternum and reshaping the chest wall is still a significant surgical operation.
What Is the Difference Between the Nuss and Ravitch Procedures?
The Nuss and Ravitch procedures are two different surgical approaches used for pectus excavatum.
In the Nuss procedure, a metal bar is placed behind the sternum to lift the chest wall forward.
In the Ravitch procedure, a more open surgical approach is used. Selected deformed costal cartilage may be removed or reshaped, and the sternum may be repositioned.
The choice between the two techniques may depend on:
- age,
- chest wall rigidity,
- deformity pattern,
- asymmetry,
- previous surgery.
Neither method is automatically better for every patient.
How Long Does the Nuss Procedure Take?
The duration of surgery varies.
Factors that may influence operating time include:
- anatomy of the deformity,
- patient age,
- chest wall rigidity,
- number of bars required,
- previous chest surgery,
- findings encountered during surgery.
There is therefore no single fixed operating time that applies to all patients.
Is the Nuss Procedure Painful?
Postoperative pain is an important aspect of recovery after the Nuss procedure.
Even though the operation is minimally invasive, the metal bar lifts and holds the chest wall in a new position, creating significant mechanical changes in the ribs, muscles, and chest wall tissues.
Pain may be most noticeable during the first days after surgery.
Depending on the patient and treatment protocol, pain management may include:
- different types of pain medication,
- regional anesthesia techniques,
- nerve blocks,
- epidural analgesia,
- intercostal nerve cryoablation.
Pain-control strategies vary between centers and patients.
What Is Cryoablation?
Cryoablation is one of the techniques that may be used to reduce postoperative pain after the Nuss procedure.
Selected intercostal nerves are exposed to controlled low temperatures to temporarily reduce pain transmission.
Nerve function gradually returns over time.
Cryoablation is not required in every patient and is only one of several possible pain-management strategies.
How Long Do Patients Stay in Hospital After the Nuss Procedure?
Hospital stay varies between patients.
Discharge generally depends on factors such as:
- adequate pain control,
- ability to stand and walk,
- stable breathing,
- adequate eating and drinking,
- absence of significant postoperative complications.
Modern pain-management protocols and early mobilization may allow shorter hospital stays in selected patients, but recovery remains individual.
When Can Patients Walk After the Nuss Procedure?
Early mobilization is encouraged when the patient’s condition allows.
Recovery generally progresses from:
- changing position in bed,
- sitting,
- standing,
- walking.
Early movement may help:
- support circulation,
- improve lung expansion,
- reduce complications related to immobility,
- support return to daily activity.
What Should Be Avoided During the First Weeks?
During the early recovery period, the chest wall and pectus bar need time to adapt to the new position.
Depending on the patient, some activities may need to be restricted.
These may include:
- sudden twisting movements,
- heavy lifting,
- forceful pushing or pulling,
- activities with a high risk of direct impact to the chest.
Activity should be increased according to the postoperative plan provided by the surgical team.
How Should Patients Sleep After Nuss Surgery?
In the early postoperative period, movements when lying down or getting out of bed should be controlled.
Some patients may find sleeping on their back more comfortable.
Sudden twisting or positions that place excessive pressure on the chest may be limited initially.
Sleep-position restrictions can usually be reduced gradually as recovery progresses.
When Can Sports Be Resumed?
Return to sports should be gradual.
The early stages of recovery may begin with walking and light daily activity.
Depending on healing, progression may include:
- normal daily activity,
- light exercise,
- running,
- strength training,
- more intensive sports.
Contact sports or activities with a risk of direct chest trauma may require special consideration while the pectus bar remains in place.
There is no single return-to-sport schedule suitable for every patient.
How Long Does the Nuss Bar Stay in Place?
The pectus bar is left in place long enough for the chest wall to remodel in its corrected position.
In many treatment protocols, the bar may remain for approximately 2 to 3 years.
However, removal timing depends on factors such as:
- age,
- growth,
- type of deformity,
- surgical technique,
- stability of the corrected chest wall.
The same removal schedule does not apply to everyone.
How Is the Nuss Bar Removed?
Bar removal is a separate surgical procedure.
Once the planned period has passed, the ends of the bar are accessed through the previous incisions or nearby areas.
The fixation system is released, and the bar is carefully removed.
Bar removal is often more limited than the original Nuss operation, but it still requires surgery and anesthesia.
Can the Chest Sink Again After Bar Removal?
The goal is for the chest wall to maintain its corrected shape after the bar is removed.
However, recurrence of pectus excavatum is possible.
Factors that may influence recurrence include:
- very early surgery,
- insufficient bar duration,
- deformity characteristics,
- chest wall structure,
- continued growth.
This is one reason why the timing of bar removal matters.
What Are the Risks of the Nuss Procedure?
As with any surgery, the Nuss procedure carries potential risks.
These may include:
- bleeding,
- infection,
- pleural fluid collection,
- lung-related complications,
- movement or rotation of the bar,
- wound problems,
- prolonged pain or sensitivity,
- reactions related to the metal implant,
- recurrence of the deformity.
Because the heart and major blood vessels lie directly behind the sternum, injury to these structures is a rare but serious potential complication.
Risk varies according to anatomy, age, previous operations, and surgical complexity.
Can the Pectus Bar Move?
Bar displacement or rotation is a recognized complication after Nuss surgery.
Different stabilization techniques are used to reduce this risk.
If significant displacement occurs, another surgical procedure may occasionally be required.
This is one reason why activity restrictions during the early recovery period are important.
Will There Be Scars After the Nuss Procedure?
The incisions are generally located on the sides of the chest and are smaller than those used in traditional open chest wall reconstruction.
However, all surgical incisions leave some degree of scar.
Scar appearance depends on:
- individual wound healing,
- skin characteristics,
- incision size,
- whether infection or wound problems occur.
The procedure should therefore not be described as “scarless.”
Does the Chest Shape Change Immediately?
When the bar is rotated during surgery, the sternum is mechanically lifted, so the chest contour changes immediately.
However, the final appearance should not be judged too early.
During the first postoperative period there may be:
- swelling,
- tissue edema,
- posture changes,
- movement restriction related to pain.
The purpose of leaving the bar in place for years is to support remodeling of the chest wall in the corrected position.
Does the Nuss Procedure Completely Correct Pectus Excavatum?
The aim of surgery is to improve the chest depression and, in appropriate patients, reduce anatomical or functional effects.
However, every deformity is different.
The degree of correction may vary particularly in patients with:
- significant asymmetry,
- complex chest wall anatomy,
- very rigid chest walls,
- previous pectus surgery.
Expected anatomical results should therefore be assessed individually.
Can the Nuss Procedure Reduce Pressure on the Heart and Lungs?
Lifting the sternum increases the front-to-back space within the chest.
In patients with mechanical compression of the heart, this may reduce external pressure.
Some patients may also show improvement in exercise capacity or cardiopulmonary measurements after correction.
However, the degree of functional improvement varies.
Expected benefits depend on the patient’s preoperative anatomy and functional findings.
Why Is Follow-Up Important After the Nuss Procedure?
Postoperative follow-up is not limited to checking the surgical wounds.
Follow-up may include assessment of:
- bar position,
- chest contour,
- pain,
- return to physical activity,
- wound healing,
- possible complications.
Long-term follow-up is also important for planning the appropriate timing of bar removal.
Frequently Asked Questions
1. What is the Nuss procedure?
The Nuss procedure is a minimally invasive operation used to correct pectus excavatum. A metal pectus bar is placed behind the sternum and rotated to lift the depressed chest wall forward.
2. Who is suitable for the Nuss procedure?
It may be considered in patients with pectus excavatum when surgery is clinically appropriate. Severity, symptoms, heart and lung effects, age, anatomy, and general health are evaluated together.
3. Is the sternum cut during the Nuss procedure?
The standard Nuss technique does not involve routinely making a large cut through the sternum or removing deformed rib cartilage. The chest is elevated with a metal bar placed behind the sternum.
4. How many bars are used?
Some patients need one bar, while others may require two or more. The number depends on chest wall anatomy and the extent of the deformity.
5. Is Nuss surgery painful?
Postoperative pain can be significant, especially in the early period. Pain management may include medication, regional techniques, nerve blocks, or cryoablation in selected patients.
6. How long does the Nuss bar stay in place?
In many patients, the bar remains for around 2 to 3 years, although the exact duration varies according to age, growth, chest wall characteristics, and surgical planning.
7. Is bar removal another major operation?
Bar removal is a separate operation performed under anesthesia. It is often less extensive than the original Nuss procedure but still requires surgical care.
8. Can patients exercise after the Nuss procedure?
Yes, but return to exercise should be gradual. Heavy lifting and activities with a risk of chest impact may be restricted during parts of the recovery period.
9. Can pectus excavatum return after the Nuss procedure?
Recurrence is possible, although it does not occur in every patient. Growth, deformity characteristics, and the duration the bar remains in place can influence recurrence risk.
10. Is the Nuss procedure better than the Ravitch procedure?
Neither technique is universally better. The appropriate method depends on age, chest wall rigidity, deformity pattern, asymmetry, and previous surgery.
Information Note:
This content is intended for general informational purposes only. Suitability for the Nuss procedure is not determined solely by the external appearance of pectus excavatum or by a single radiological measurement. The anatomy of the deformity, age, growth stage, symptoms, possible effects on the heart and lungs, and overall health should be considered together. The surgical technique, number of bars, pain-management strategy, activity restrictions, and timing of bar removal may vary between patients. The information provided here does not replace individual medical assessment, diagnosis, or treatment planning.